| Study | Design & population | Finding & comparison |
|---|---|---|
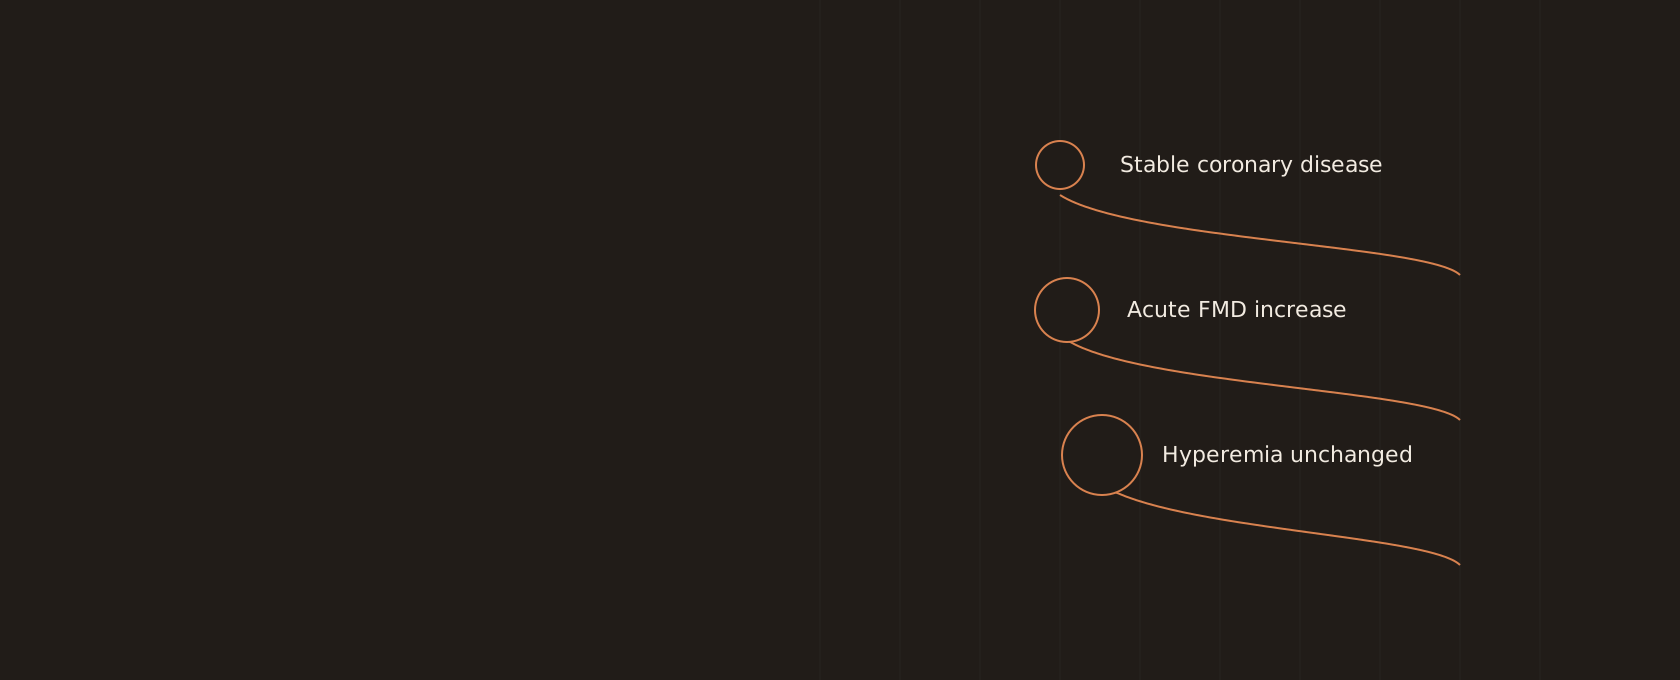
| 2021 · Gravel H ↗ | acute before-and-after physiological experiment stable coronary artery disease Participants: 22. Finnish sauna | Flow-mediated dilation increased after exposure while reactive hyperemia did not significantly change. Comparison: before versus after Small acute study; stable disease only; no clinical-event comparison. |
| 2019 · Gravel H ↗ | Randomized crossover physiology trial Healthy middle-aged and older adults Participants: 21. Finnish sauna | Neither sauna pattern significantly improved the measured flow-mediated dilation or reactive-hyperemia endpoints acutely. Comparison: Seated time control Small healthy sample |
| 2023 · Debray A ↗ | randomized controlled trial Stable coronary artery disease Participants: 41. Finnish sauna · 8 weeks | Heat-acclimation measures changed, but endothelial function, stiffness and blood-pressure changes did not favor sauna over control. Comparison: Lifestyle maintenance Small stable-CAD sample |
Original publication: Acute Vascular Benefits of Finnish Sauna Bathing in Patients With Stable Coronary Artery Disease.
The clinical setting defines the question
The study tested whether Finnish sauna acutely changed peripheral flow-mediated dilation in middle-aged and older adults with stable coronary artery disease. Flow-mediated dilation, or FMD, measures an artery’s diameter response to a standardized increase in blood flow. It is a physiological test relevant to endothelial function, rather than a direct measurement of future cardiac events.
The original publication is Acute Vascular Benefits of Finnish Sauna Bathing in Patients With Stable Coronary Artery Disease. Stable disease is an essential qualification. The result does not establish suitability during an unstable cardiac condition or describe what every person with a coronary diagnosis would experience. Its value is a focused observation in a clinical population, which should remain separate from a general recommendation for sauna use.
Before and after is the assigned contrast here
Participants completed sauna exposure separated by rest, and the researchers evaluated vascular measurements before and after the session. The indexed abstract describes a before-and-after comparison rather than an equivalent unheated condition. That lets the study characterize a response around exposure but leaves uncertainty about what would have changed over similar time without sauna.
Rest, testing order and repeat measurement are possible influences in an acute experiment. A controlled comparison would help distinguish them from heating. This design issue should not obscure the actual observation, but it should shape the conclusion drawn from it. The experiment can support a claim about measured post-session change; a stronger statement that heat alone caused a durable improvement would require additional comparison and follow-up.
The FMD finding was favorable
Brachial artery FMD increased after exposure in the reported analysis. That is the qualitative result retained in the verified fact registry. The observation is worth including because it differs from a controlled acute study in healthy older adults that did not demonstrate an FMD improvement.
The term improvement refers here to the measured response under the experimental conditions. It does not establish structural repair of the artery or reversal of coronary disease. A short-term test can change without showing that an intervention will prevent events over ordinary life. Keeping that scope explicit avoids losing either side of the finding: the favorable vascular measurement is real within the report, while its clinical translation and persistence remain questions rather than established consequences.
Reactive hyperemia did not show the same response
Postocclusive reactive hyperemia did not significantly change. This measures the flow response after a brief interruption of circulation and is distinct from the diameter-based FMD endpoint. The same session therefore did not produce a uniformly favorable result across every vascular test.
A summary that mentions only increased dilation would omit a useful limit on a broad vascular-health claim. Conversely, unchanged hyperemia does not cancel the reported FMD result. Different tests probe different responses and can vary in sensitivity and precision. The correct synthesis preserves both outcomes without turning the paper into a binary label of success or failure. Researchers and readers can then ask which mechanism is supported, which remains uncertain and whether further controlled work reproduces the pattern.
Healthy older adults had a different acute result
A randomized crossover study in healthy middle-aged and older adults compared sauna conditions with seated rest and did not find significant acute improvement in its FMD or reactive-hyperemia endpoints. Its control condition and participant health differ from the present clinical experiment, so the findings are not estimates of a perfectly identical effect.
The comparison is valuable precisely because it highlights those differences. Baseline vascular function, experimental timing and the presence of an unheated condition may matter, but the abstracts do not establish which factor explains the disagreement. A careful appraisal should not invent a reassuring explanation. It should describe the contrasting results and identify the further work needed to distinguish population effects from protocol or measurement effects.
The repeated coronary-disease trial sets another boundary
The randomized trial of a repeated Finnish sauna program in stable coronary disease did not find vascular-marker changes favoring sauna over lifestyle maintenance. Heat-acclimation measures changed, but the proposed vascular advantage was not demonstrated. That is directly relevant context for anyone tempted to infer a lasting benefit from this acute FMD observation.
An immediate post-session response and a repeated-program change are different outcomes. The acute study cannot predict that the favorable test will persist, while the longer trial does not erase the earlier within-session observation. Together they show why mechanism development needs sequential tests rather than a leap from one promising marker to a prevention claim. An assigned repeated program deserves its own results even when those results complicate the original hypothesis.
What further evidence would resolve the uncertainty
A stronger acute test would compare sauna with an unheated condition under similar timing and measurement procedures. Longer follow-up could ask how long the FMD response lasts, while independent clinical samples would help test reproducibility. These design improvements address different uncertainties and should not be treated as interchangeable.
Patient-important outcomes would require separate investigation. An artery-dilation test is not a count of angina episodes, admissions or deaths. The current emerging grade therefore concerns a plausible but limited physiological signal, with unconfirmed translation. The paper is most useful when the question is kept narrow: in this selected stable-disease sample, did the measured vascular response change after exposure? It is less suited as a foundation for claiming that a home sauna improves coronary prognosis.
Review scope, disclosure and personal safety
The indexed abstract was refreshed and compared with the stored corpus and fact statement. PubMed and the DOI identify the original source. This is not a full-text review of measurement quality, eligibility, funding or competing interests. Information absent from the reviewed material has not been filled from assumptions.
Personal safety is a separate question from the direction of FMD. The cited narrative review names unstable angina, recent myocardial infarction and severe aortic stenosis as contraindications and warns about alcohol-related concerns. Its list is not comprehensive clearance. The selected stable-disease experiment does not justify reproducing its exposure without considering an individual’s condition and medications with a qualified clinician. Its contribution remains an acute source-specific observation rather than a clinical protocol.
Explore the evidence with a tool.
Questions, considered
Questions about this study
Did every vascular measure improve in the stable-coronary-disease sauna experiment?
No. Flow-mediated dilation increased after exposure, whereas the reported reactive-hyperemia measures did not change significantly. These are distinct physiological tests. Describing the findings as uniform vascular improvement would omit the null results and imply a broader effect than the measurements support in this small acute experiment.
Follow the sourceDid the stable-coronary sauna experiment establish long-term cardiovascular protection?
No. It measured physiological responses before and shortly after a sauna exposure. The study did not count subsequent heart attacks or deaths as its tested outcome. Improved flow-mediated dilation is a mechanistic observation, rather than direct proof of fewer cardiovascular events or lasting benefit.
Follow the sourceCan the stable-coronary experiment be generalized to unstable cardiac symptoms?
No. The participants had stable coronary artery disease, which is an important boundary of the evidence. The findings do not establish responses during unstable symptoms or an acute coronary event. The study’s controlled clinical context and selected population should remain explicit in any practical discussion.
Follow the sourceFollow the evidence
Sources & references
Research summaries in this edition are based on indexed abstracts unless otherwise noted. A source link is not a claim of medical review.
- Acute Vascular Benefits of Finnish Sauna Bathing in Patients With Stable Coronary Artery Disease.
Gravel H, Behzadi P, Cardinal S, Barry H, Neagoe PE, Juneau M, Nigam A, Sirois MG, Gagnon D
Volume 37, issue 3, pages 493-499 · PMID 32615263
Open-access flag: not recorded.Abstract-level editorial review - Acute effect of Finnish sauna bathing on brachial artery flow-mediated dilation and reactive hyperemia in healthy middle-aged and older adults.
Gravel H, Coombs GB, Behzadi P, Marcoux-Clément V, Barry H, Juneau M, Nigam A, Gagnon D
Volume 7, issue 13, pages e14166 · PMID 31293098
Open-access flag: yes.Abstract-level editorial review - Finnish sauna bathing and vascular health of adults with coronary artery disease: a randomized controlled trial.
Debray A, Gravel H, Garceau L, Bartlett AA, Chaseling GK, Barry H, Behzadi P, Ravanelli N, Iglesies-Grau J, Nigam A, Juneau M, Gagnon D
Volume 135, issue 4, pages 795-804 · PMID 37650138
Open-access flag: not recorded.Abstract-level editorial review - Benefits and risks of sauna bathing.
Hannuksela ML, Ellahham S
Volume 110, issue 2, pages 118-126 · PMID 11165553
Open-access flag: not recorded.Abstract-level editorial review