| Study | Design & population | Finding & comparison |
|---|---|---|
| 2023 · Debray A ↗ | randomized controlled trial Stable coronary artery disease Participants: 41. Finnish sauna · 8 weeks | Heat-acclimation measures changed, but endothelial function, stiffness and blood-pressure changes did not favor sauna over control. Comparison: Lifestyle maintenance Small stable-CAD sample |
| 2022 · Lee E ↗ | randomized controlled trial Low activity with at least one cardiovascular risk factor Participants: 47. postexercise sauna · 8 weeks | Relative to exercise alone, exercise plus sauna produced an additional fitness change of +2.7 mL/kg/min (95% CI +0.2 to +5.3) and a systolic-pressure difference of −8.0 mmHg (−14.6 to −1.4). This small combined-program trial did not test sauna alone or clinical-event prevention. Comparison: Exercise alone; control Small eight-week multi-arm trial |
| 2021 · Pizzey FK ↗ | Systematic review and meta-analysis Healthy and clinical populations Mixed heat therapy · 10–36 sessions | Pooled blood-pressure and flow-mediated-dilation changes favored heating; resting heart rate did not significantly change, and certainty varied by outcome. Comparison: Control conditions Different populations and heat methods |
Original publication: Finnish sauna bathing and vascular health of adults with coronary artery disease: a randomized controlled trial.
The trial tested a proposed vascular explanation
This study tested whether a repeated Finnish sauna intervention improved vascular measurements in adults with stable coronary artery disease. It was designed to examine a possible explanation for favorable observational sauna associations. Its value is therefore unusually direct: rather than assuming a vascular mechanism from a cohort headline, it measured several candidate endpoints after an assigned program.
The original publication is Finnish sauna bathing and vascular health of adults with coronary artery disease: a randomized controlled trial. Stable coronary disease defines the clinical setting. The participants were not a general sample of all sauna users, and the study did not test exposure during an unstable cardiac episode. This summary keeps that population visible because neither a favorable finding nor a null one can automatically be transferred to every reader with a cardiovascular concern.
The control condition defines the comparison
Participants were randomized to sauna use or lifestyle maintenance. Comparing changes between those assigned groups is more informative for a causal question than simply asking whether the sauna group changed from its own baseline. A measurement can move over time in both groups, or differently because of influences unrelated to the intended intervention.
The relevant question is therefore whether the sauna program produced an advantage over the comparison condition for the prespecified vascular tests. Randomization supports that comparison but does not make a small trial immune to uncertainty. Precision, adherence, measurement quality and the duration of observation still matter. This abstract-level appraisal does not independently assess all of those features from the full protocol. It identifies the assigned contrast and distinguishes it from the unassigned habits in a long-term cohort.
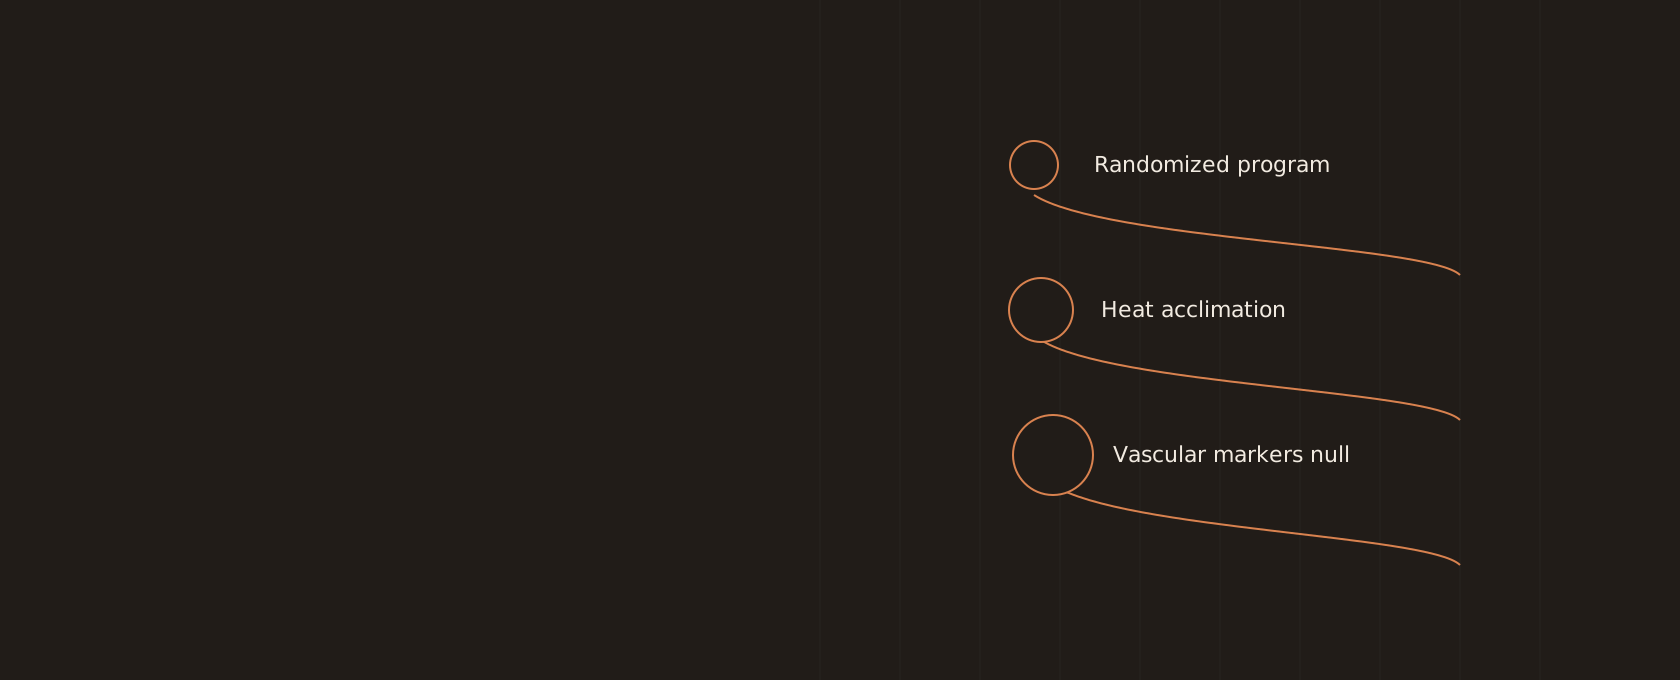
Heat acclimation was demonstrated
Some measurements changed in a way consistent with adaptation to repeated heat exposure. The verified source interpretation records heat-acclimation changes while separating them from the vascular endpoints. This distinction is central to the paper because it shows that an intervention can affect thermoregulatory responses without delivering every proposed cardiovascular benefit.
Heat acclimation should not be used as a substitute outcome when a vascular hypothesis fails to receive support. It can demonstrate that the exposure was physiologically meaningful, but that is a different question from whether endothelial function, arterial stiffness or blood pressure improved relative to control. Readers should therefore avoid a broad phrase such as the sauna worked unless the intended endpoint is stated. In this trial, adaptation to heat and improvement in the tested vascular markers were not equivalent findings.
The vascular-marker result did not favor sauna
The changes in endothelial-function, arterial-stiffness and blood-pressure measures did not favor sauna over control. That is the principal conclusion retained in the site’s fact record. The result is important counterweight to a claim that repeated Finnish sauna necessarily improves these vascular markers in people with coronary disease.
The null findings should not be hidden behind the favorable heat-acclimation result. They should also not become a claim that no sauna-related health effect could exist under any conditions. The study tested defined measurements in a selected population over its intervention period. It did not measure whether participants later experienced fewer clinical events. The useful conclusion is endpoint-specific: the repeated program did not demonstrate the proposed vascular advantage in this stable-coronary-disease sample.
A favorable exercise combination trial is a different test
Another randomized study reported favorable fitness and systolic-pressure changes when sauna was added to an exercise program, compared with exercise alone. Its participants were less active adults with cardiovascular risk factors, and the intervention deliberately combined two components. That trial therefore addresses an add-on question rather than the same standalone sauna question tested here.
The differing results should prompt comparison of population, baseline status, exposure and endpoints rather than a search for whichever study supports a preferred conclusion. A combined program may operate differently from sauna alone in established coronary disease. The abstracts do not establish which difference explains the disagreement. Keeping both studies in view is more informative than averaging their conclusions into an assertion that sauna reliably lowers blood pressure in every clinical setting.
How a favorable review fits with a later null trial
A systematic review and meta-analysis of mixed heat therapies reported pooled blood-pressure and flow-mediated-dilation changes favoring heating, while certainty varied by outcome. Such a synthesis can describe the earlier collection of eligible studies. It does not guarantee that every later trial, intervention or population will show a favorable result.
The present trial provides more specific evidence for repeated Finnish sauna in stable coronary disease. Its findings should be added to the evidence picture rather than dismissed because an earlier pooled result was positive. Conversely, a single later null trial does not automatically overturn every pooled estimate from different heat methods. The comparison highlights the need to inspect eligibility criteria, review dates and population differences before transferring a general heat-therapy conclusion to a particular sauna decision.
What remains unsettled after randomization
The randomized design improves the test of an assigned intervention, but the sample and follow-up still limit what can be concluded. A small surrogate-endpoint trial cannot establish the effect on long-term mortality or every clinical event. It also cannot demonstrate safety in conditions that were not represented by its stable-disease population.
Future work could investigate different durations, populations or combinations of activity and heat. Those are possible research directions, not known reasons to disregard the observed null result. The emerging evidence grade reflects both a stronger allocation design and limited precision and applicability. For an individual reader, the practical lesson is to keep clinical care separate from research curiosity: a physiologically active sauna regimen has not thereby earned a vascular-benefit promise.
Access, disclosure and safety boundaries
The indexed abstract was rechecked live against the corpus and fact record. Readers can follow the publication through its PubMed entry and DOI. Full-text allocation details, adherence information, funding and conflicts of interest have not been independently audited in this summary. A blank funding field means that information was not established from the reviewed material.
The separately cited safety review identifies unstable angina, recent myocardial infarction and severe aortic stenosis as contraindications and warns about alcohol-related harms. It is a historical narrative source, not a complete modern clearance protocol. Stable trial participation should not be generalized to unstable disease or used to bypass individual clinical advice. This source summary is designed to clarify the evidence, including a result that challenges a simple vascular-benefit story.
Explore the evidence with a tool.
Questions, considered
Questions about this study
Did the stable-coronary-disease sauna trial improve vascular markers?
The trial did not show improvements in the principal vascular markers or blood pressure relative to its control condition. Some heat-acclimation measures changed, which demonstrates that physiological adaptation and vascular benefit are distinct questions. A summary should include this null finding rather than relying only on positive cohort associations.
Follow the sourceDid the coronary trial study unstable heart symptoms?
No. Participants had stable coronary artery disease and were selected for the study. Its results cannot establish safety for new chest pain, unstable angina or a recent acute event. People with cardiac symptoms need clinical assessment rather than interpreting participation by stable patients as general permission to use a sauna.
Follow the sourceCan improved sweating in the coronary trial be described as improved heart health?
Not by itself. The study observed changes consistent with heat acclimation, including sweating capacity, while its vascular outcomes did not clearly improve. These measures answer different questions. Becoming more physiologically accustomed to heat does not automatically demonstrate fewer cardiovascular events or durable improvement in the vascular system of sauna users.
Follow the sourceFollow the evidence
Sources & references
Research summaries in this edition are based on indexed abstracts unless otherwise noted. A source link is not a claim of medical review.
- Finnish sauna bathing and vascular health of adults with coronary artery disease: a randomized controlled trial.
Debray A, Gravel H, Garceau L, Bartlett AA, Chaseling GK, Barry H, Behzadi P, Ravanelli N, Iglesies-Grau J, Nigam A, Juneau M, Gagnon D
Volume 135, issue 4, pages 795-804 · PMID 37650138
Open-access flag: not recorded.Abstract-level editorial review - Effects of regular sauna bathing in conjunction with exercise on cardiovascular function: a multi-arm, randomized controlled trial.
Lee E, Kolunsarka I, Kostensalo J, Ahtiainen JP, Haapala EA, Willeit P, Kunutsor SK, Laukkanen JA
Volume 323, issue 3, pages R289-R299 · PMID 35785965
Open-access flag: yes.Abstract-level editorial review - The effect of heat therapy on blood pressure and peripheral vascular function: A systematic review and meta-analysis.
Pizzey FK, Smith EC, Ruediger SL, Keating SE, Askew CD, Coombes JS, Bailey TG
Volume 106, issue 6, pages 1317-1334 · PMID 33866630
Open-access flag: not recorded.Abstract-level editorial review - Benefits and risks of sauna bathing.
Hannuksela ML, Ellahham S
Volume 110, issue 2, pages 118-126 · PMID 11165553
Open-access flag: not recorded.Abstract-level editorial review